Researchers have identified early molecular warning signs of inflammatory bowel disease (IBD) that can appear before symptoms surface and remain actively detectable even when patients appear to be doing well. The groundbreaking study, led by the Walter and Eliza Hall Institute of Medical Research (WEHI) in partnership with the Royal Melbourne Hospital, has uncovered a hidden defect in intestinal cells that leaves them inherently vulnerable to damage. Crucially, this underlying problem was still identifiable in patients whose chronic gastrointestinal conditions appeared to be well-controlled by modern medical therapies.
Published in the prestigious scientific journal Science, the findings offer a vital piece of the puzzle regarding why individuals living with inflammatory bowel disease can experience sudden, debilitating flare-ups even after achieving what doctors classify as clinical remission. By examining human tissue at a microscopic level, the research team has shed light on mechanisms that were previously obscured by the limitations of traditional medical observation and animal models, opening up entirely new avenues for future monitoring and personalized care.
A Hidden Problem in Intestinal Cells
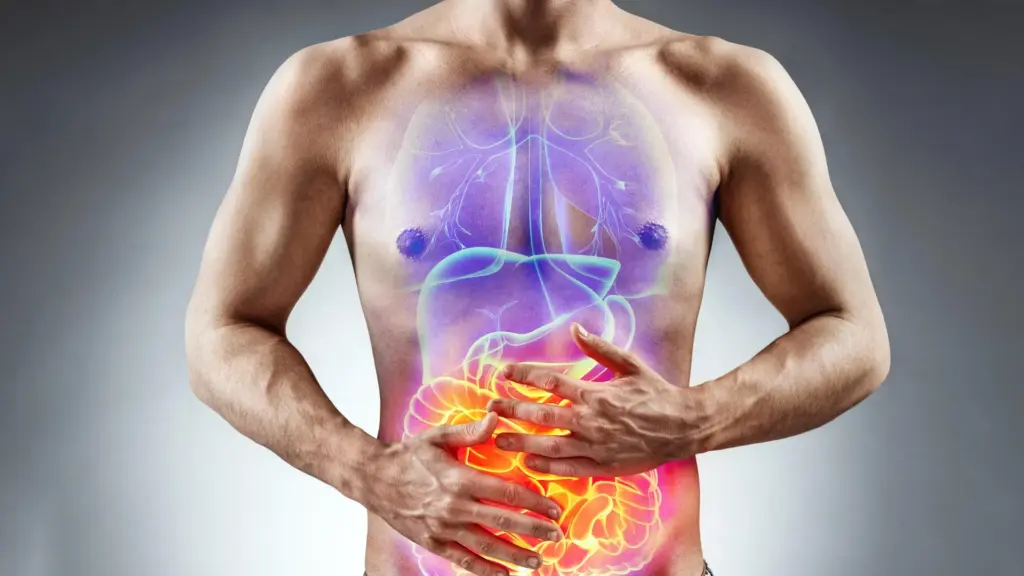
Inflammatory bowel disease, which broadly encompasses chronic conditions such as Crohn’s disease and ulcerative colitis, affects approximately 180,000 Australians and millions more worldwide. It is characterized by a relapsing and remitting course that can severely disrupt the daily lives of those affected. People living with IBD frequently experience distressing and painful symptoms, including recurring rectal bleeding, severe abdominal pain, persistent diarrhea, chronic fatigue, and substantial, unintended weight loss.
While modern pharmaceutical therapies have revolutionized care and successfully helped many patients achieve periods of clinical remission, diagnosing and managing IBD remains an exceptionally complex challenge for gastroenterologists. The disease notoriously alternates between quiescent periods, when symptoms are well-managed or absent, and sudden flare-ups that can escalate rapidly, occasionally becoming severe enough to require emergency hospital care, intensive monitoring, or surgical intervention.
Dr. Andre Samson, a study co-author from WEHI, explained that the research team discovered intestinal cells could remain vulnerable and primed for destruction even when patients felt entirely well and their clinical disease parameters appeared stable. Once an individual receives a diagnosis of IBD, the condition is lifelong. Even if a patient becomes completely symptom-free on their current medication regimen, clinicians have long known that there remains a high statistical likelihood of a future flare or relapse.
Elaborating on what the team observed in patient samples, Dr. Samson noted that intestinal cells are essentially primed to die prematurely. Even in patients exhibiting virtually no clinical symptoms, this persistent cellular vulnerability remains sitting quietly beneath the surface, waiting for a trigger or progression that tips the balance toward active inflammation.
Cell Death May Help Drive IBD
These new results challenge a long-held assumption within the medical community: that cell death in inflammatory bowel disease is simply collateral damage caused by pre-existing inflammation. Instead, the researchers propose that abnormal, premature cell death may be actively involved in driving the disease process itself, acting as an initiator rather than merely a byproduct.
Significantly, this cellular defect was already present during the absolute earliest stages of disease activity, including in patients whose IBD was clinically mild. Detecting such a subtle anomaly required exceptionally detailed molecular analysis of human tissue, separating it from the surrounding cellular noise.
Professor James Murphy, a WEHI deputy director, lab head, and co-author of the study, stated that this discovery revealed a "smoldering" molecular problem. This realization has encouraged the research team to focus much more closely on the earliest events that occur at the absolute beginning of the disease trajectory, long before clinical manifestation.
Professor Murphy pointed out that the vast majority of historical research has focused on the major clinical crisis point, which occurs when a patient arrives at the hospital suffering from severe, acute gut inflammation. By contrast, the research team deliberately went to the opposite end of the clinical spectrum to examine gut tissue that lacked clear signs of active disease. What they uncovered was a molecular defect manifesting very early in the progression of the condition—effectively representing one of the very first dominoes to fall in the cascade of IBD pathology.
Human Tissue Reveals Clues to Future Flare-Ups
A critical strength of the research is that it relied entirely on human tissue and patient-derived organoids rather than relying solely on traditional laboratory models. Working in close collaboration with expert clinicians from the Royal Melbourne Hospital, the investigative team collected approximately 900 distinct biopsies from a cohort of 80 individuals, comprising both people with IBD and healthy controls.
Researchers utilized these precious clinical samples to successfully grow organoids—three-dimensional, lab-grown tissues derived directly from patients. This innovative technique allowed the team to investigate the biology of the disease directly within living human cells, capturing the true complexity of human physiology.
Professor Edwin Hawkins, head of the Colonial Foundation Diagnostics Center where the samples were analyzed and a WEHI lab head, emphasized the importance of using human tissue. While cell death has long been suspected of playing a role in IBD, exactly how it arises within humans has remained poorly understood for decades. Professor Hawkins noted that this knowledge gap likely persisted because the vast majority of previous studies relied heavily on mouse models, which frequently fail to accurately mimic the nuances of the human condition. By basing their study directly on human biopsies and patient-derived cells, the researchers bypassed these translational barriers.
Following the initial tissue collection, the research team tracked the participating patients for a period exceeding two years. Their longitudinal tracking revealed a striking clinical correlation: individuals who displayed stronger intestinal cell death signaling at the molecular level were significantly more likely to experience a clinical relapse during the follow-up period.
Toward Earlier IBD Detection
Inflammatory bowel disease is notoriously heterogeneous, meaning it can behave wildly differently from one person to another. This variability makes it exceptionally difficult for physicians to predict which patients will respond favorably to a specific therapeutic agent, or which individuals are at the highest risk of an impending relapse.
Dr. Jiyi Pang, another study co-author, explained that these newly identified molecular signals could eventually assist scientists and clinicians in developing much more precise diagnostic and monitoring tools. Such advancements would allow physicians to select treatments based on the unique biological characteristics of an individual patient’s disease rather than relying on a trial-and-error approach.
Dr. Pang highlighted that the fundamental causes of IBD remain largely unknown and are remarkably variable across the patient population. By utilizing mini-intestinal organoids grown in specialized dishes and fostering a collaborative, multi-disciplinary team of researchers and clinicians, the team successfully pinpointed the specific inflammatory signals responsible for driving this aberrant cell death response.
With these findings, science now possesses clearer hallmarks of what underlies the disease at the foundational molecular level. The next critical question for translational researchers is determining which of these pathways are therapeutically actionable, and whether they can be leveraged to precisely match medical treatments to patients based on how their specific disease behaves molecularly.
More Personalized Treatment Could Follow
While the implications of the study are profound, Dr. Aysha Al-Ani offered a note of caution, pointing out that the discoveries are unlikely to yield an immediate new diagnostic test or pharmaceutical therapy overnight. However, the findings provide a robust, scientifically rigorous foundation for future research aimed at developing superior forecasting tools and targeted interventions.
Dr. Al-Ani noted that the work opens entirely new avenues for developing prognostic tools that utilize significantly more sophisticated and refined methods than those currently available in standard clinical practice. The overarching ethos behind modern IBD therapy is to reduce the frequency and severity of debilitating flares, halt long-term disease progression, and ultimately improve the quality of life for patients. Implementing more sensitive molecular detection methods in the future may eventually help clinicians keep patients in deep, sustained remission for much longer periods while introducing novel therapeutic strategies before clinical symptoms manifest.
The comprehensive research endeavor was supported by a wide network of academic and medical institutions. The research team included scientists and clinicians hailing from the University of Melbourne, the Royal Melbourne Hospital, the Royal Children’s Hospital, the Monash Institute of Pharmaceutical Sciences, the Hudson Institute of Medical Research, and Monash University.
Financial backing for the study was provided by a coalition of philanthropic and governmental bodies, including the Kenneth Rainin Foundation, the National Health and Medical Research Council of Australia (NHMRC), the Australian Research Council, the Stafford Fox Medical Research Foundation, the Colonial Foundation, Crohn’s and Colitis Australia, and the Victorian State Government.